


You have 10 small joints in your lower back that you’ve never once thought about.
They sit at the back of the spine, a pair at every level, and they’re the reason you can bend down to tie a shoe and lean back to look at the ceiling but can’t wring your lower half around like a wet towel. They’re called the facet joints. They’ve been doing that quietly every day you’ve been alive.
I’d never heard of them either. They turn out to be the hero of this story.
Because sometimes a lower back comes apart. The cushion between two bones wears through and they start to grind, or one slips forward over the one underneath, and that little section goes loose. When it gets bad enough, surgeons fuse it. They lock the two bones together until they knit into one piece and the grinding stops. More than 400,000 of those a year in America, and it works. It has worked for 60 years, and it’s why hundreds of thousands of people are walking around today without pain.
Then I read how they hold the bones still while that happens. Four screws, two metal rods. And running down the middle of your spine is a hollow channel carrying the wiring for everything below your waist, legs and bladder and bowel, all of it taking orders through that one tunnel. The screws go into the bone on either side of it. Every one of them passes within millimeters of the nerves, and surgeons breach the wall on the nerve side in 20 to 40% of cases.
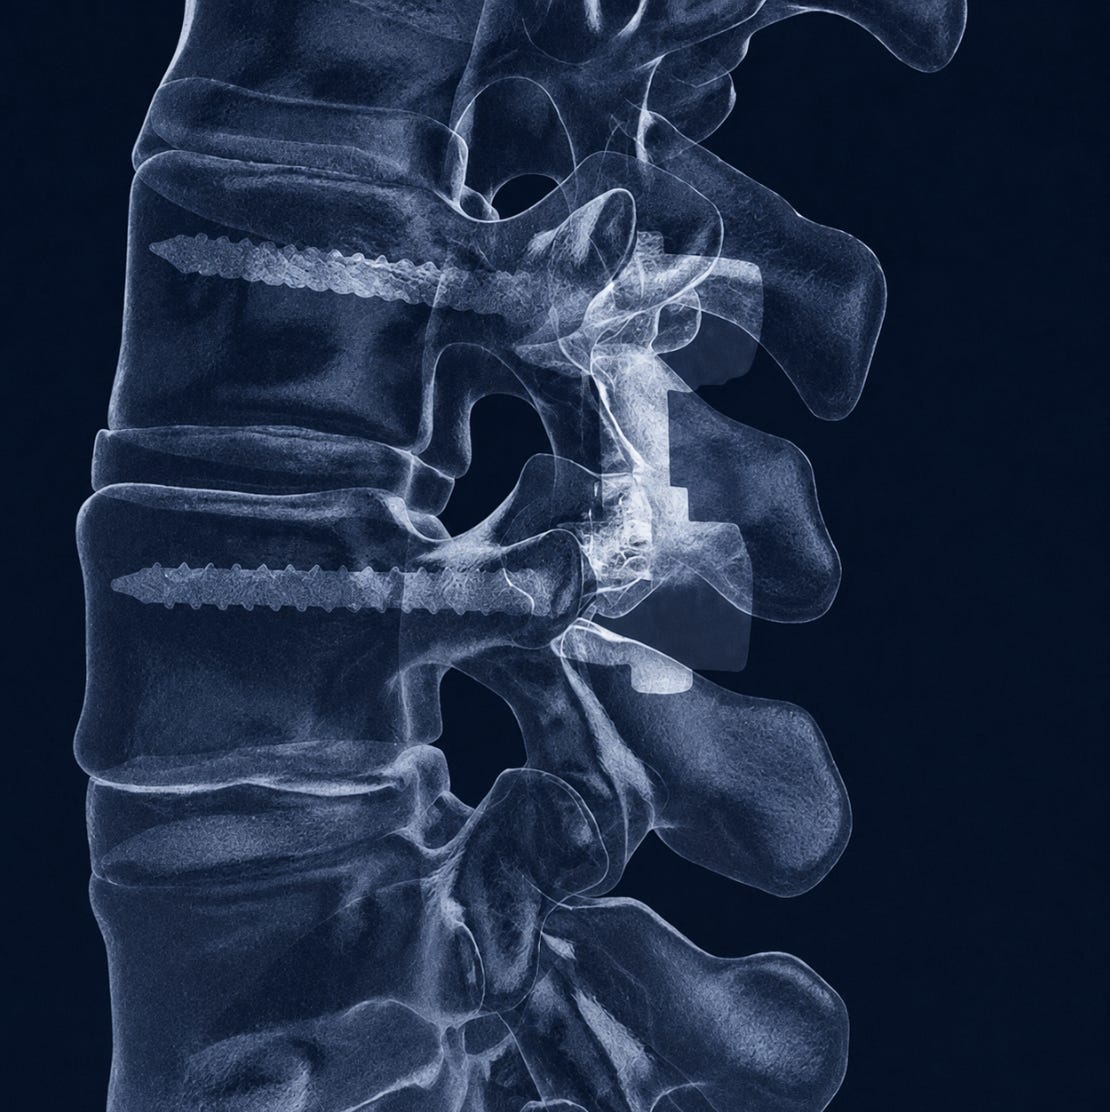
That number stopped me, though not for the reason you’d think. Surgeons know it, they plan around it, and most of those breaches never bother anybody. What got me is what it says about the tool. Sixty years, the best minds in orthopedics, and the screw still wanders that often, because of where it’s forced to go.
That’s the deal, and it’s been the only deal on the table since the 1960s. Every improvement anyone made in all that time was a better screw.
Nobody made a different shape.
First You Have to Fail Everything Else
This takes years to arrive at. It starts as an ache low in the back that just won’t quit, and then one morning it’s running down a leg. You stop carrying things. You start planning the day around how long you’ll be on your feet. You find the one chair in the house that works, and eventually you’re sleeping in it, because lying flat turned out to be worse.
Then come the months of physical therapy. Then the injections. Then whatever your doctor wants to try after that. And here’s something I didn’t know until I went looking: in America you’re not even allowed to have this operation until all of it has failed. “Failed conservative care” is written right into the FDA’s own paperwork. It’s a requirement.
So by the time anyone offers to fix it, you’ve been hurting for years. And then you hear what fixing it involves. To get at the bone, the surgeon peels the muscle off your spine. Six incisions. A hospital bed. And then months, real months, before you feel like yourself again. If you’ve ever watched somebody you love go through this, you know that’s the part nobody warns you about. You don’t remember the surgery. You remember the winter afterward, and how carefully they got out of a chair.
Most breached screws never bother anybody, and the nerve roots down there are more forgiving than the spinal cord higher up, so this isn’t a catalogue of horrors. But when a breach runs deep, the published series report nerve pain down a leg, or weakness, or going back under to have the screw pulled out.
People say yes to all of it anyway. They say yes because the alternative is a pain that has already taken the job, the sleep and the Sunday afternoons, and is coming back for whatever’s left.
And they go through the pedicles because that’s where the good bone is. The pedicle is a short stalk of dense bone joining the front of a vertebra to the back, and it’s the strongest anchor a surgeon can reach from behind. The safest grip happens to sit in the most dangerous neighborhood.
There’s one more cost, and it’s the strangest fact in this story. Putting those screws in damages the facet joint above the fusion, one of the 10 I just introduced you to, in something like 18% of placements, a joint that was never part of the operation.
Pedicle screws are a trade, and for 60 years it was the only trade on offer.
Built in Israel is a reader-supported publication. To receive new posts and support my work, consider becoming a free or paid subscriber.
They Solved This in 1948. Then They Walked Away.
Back to those 10 joints. In the lower spine they’re the only true joints you have, the place the hinging actually happens, and they’re what holds each section steady. They also sit at the back, well away from the channel, which makes them both the obvious thing to lock and a short walk to reach.
So go in through the joint. Obvious, right? Surgeons thought so too, in 1948.
A surgeon named King fused a lumbar spine that year by running short screws straight across the facet joints. Boucher lengthened them in 1959. And in 1984 a Swiss surgeon named Friedrich Magerl published the version everyone settled on, a longer screw entering from the far side and crossing the joint. A series of 88 fusions using his technique came back with solid fusion in 91% of patients, short operating times, few complications.
Magerl was right. He had found the door, it was the cheap one, and it was nowhere near the nerves. And within a few years his own profession put it down.
Roy-Camille had performed the first pedicle screw fixation in Paris in 1963, and through the 1980s pedicle screws spread like weather, because they’re strong enough for anything you throw at them: multiple levels, deformity, a badly slipped vertebra. Facet screws couldn’t compete on range. The word a review published this year uses is surpassed.
Range was half of it. The other half was shape. A screw is a straight rigid line. A facet joint is small and curved and built differently in every patient, and differently on each side of the same patient. Push a straight thing through a curved thing you can’t fully see and you get what the literature records: screws breaking through the bone wall, and an articular process fractured under the drill, pinching a nerve root, the patient going back for pedicle screws anyway.
So a Swiss surgeon spent his career finding the safest route into the spine, proved it worked, and had to watch it get shelved because the only tool anyone could make was the wrong shape for it.
The Man Who Built a Better Screw Twice
Uri Arnin arrived in medical devices at 45, by accident, out of a career spent on materials. Machining metal, coating it, injecting it into molds, plastics and polymers, the sort of engineering that has nothing to do with the human body and everything to do with what a material does when you lean on it. He looked around orthopedics, decided hips and knees were handled, and went after the part that wasn’t.
He found the facets coming at it from the opposite side to the surgeons. Studying who was getting fused, he kept seeing people whose cushions were perfectly fine. The trouble was all in the back of the spine, and the operation fused the whole section anyway, healthy disc included.
His first answer was a facet joint replacement called TOPS, the first in the world, built at an Israeli company called Impliant. It mounted on four pedicle screws.
The man who had worked out that the joint was the problem still hung his answer on the same four screws as everybody else. In 2003 that was simply how you attached a thing to a spine.
That was his better bandage.
Impliant put north of $50 million into it and closed its doors in June 2010, wiped out by the financial crisis. Somebody else bought the assets out of the wreckage and carried that device across to an FDA approval 13 years later, under a different company’s name.
Most people would have stopped there. Failing that, they’d have stopped doing spines. He went and built the first remote-controlled spinal implant, then founded ApiFix, which straightens the backs of teenagers with scoliosis, and sold it in 2020. Twenty-nine patents issued and 43 pending, every one of them in the spine. The man has spent 30 years picking at the same six inches of the human body.
And when a trade journal asked how he picks his problems, he gave an answer I didn’t expect from somebody with that record. He said he isn’t cleverer than the thousands of engineers working the same problems everywhere else, many of them at bigger companies with more money. So when he takes something on, he has to bring a tool that wasn’t available two years ago. Otherwise, why would he be the one to crack it?
He had a track record, an exit and nothing left to prove. In 2017 he went back to the joint a third time.
And he brought a surgeon. ZygoFix was founded that year at a business park in the Galilee hills of northern Israel, inside an incubator run by Trendlines, on money from the Israel Innovation Authority. His co-founder was Professor Yizhar Floman, who chairs the Israel Spine Center at Assuta in Tel Aviv, ran spine surgery at Hadassah in Jerusalem before that, and served as president of the Israel Orthopedic Association.
A man who had spent his entire career placing the screws they were now trying to make unnecessary.
Everyone Else Was Aiming the Screw Better
The spine industry is enormous, and it spent those 40 years making the pedicle screw safer. Better imaging. CT scanners wheeled into the operating room. Navigation systems that track the screw’s path on a monitor in real time. Surgical robots that hold a trajectory steadier than any human wrist. Billions of dollars and some of the finest engineering in medicine, and it worked, and the meta-analyses show navigated and robotic screws do land more accurately than a surgeon’s freehand. I’ve written here before about one of those companies, an Israeli one, whose headset lets a surgeon see the path through the skin. They’re superb at what they do.
What they do is put the screw in the right place.
Two men in the Galilee hills asked a different question. What if you don’t need the screw? The 3D printer is what let them answer it.
Printing makes an object you cannot machine on a lathe: one piece of titanium, rigid where it carries load and bendable where it has to conform, so it goes in straight and takes the joint's own shape on the way. They called it zLOCK. The company calls the design self-conforming, and says it's the only implant that conforms to the facet anatomy during insertion, with stability comparable to a pedicle screw construct.
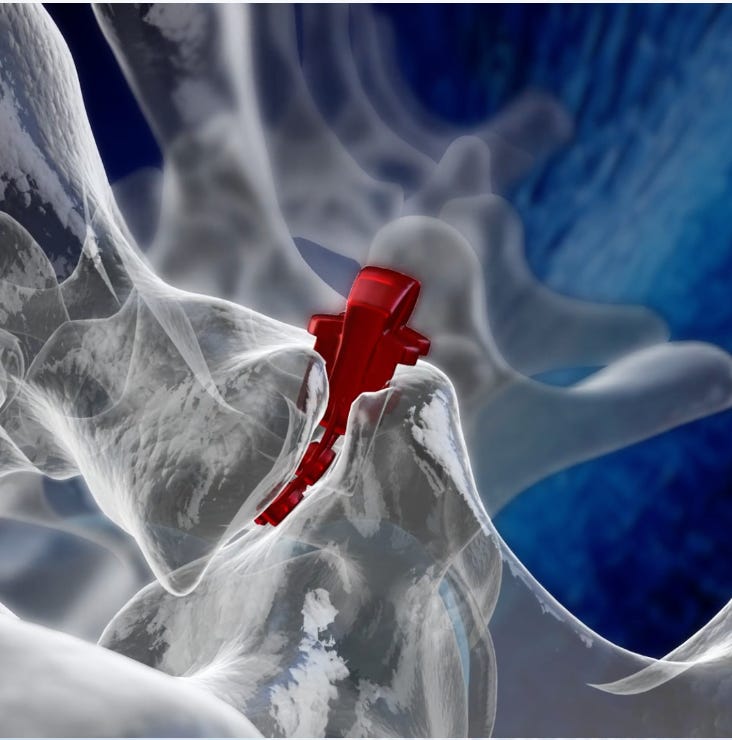
Magerl couldn’t have built this. Neither could King in 1948, or Arnin himself in 2003. It’s a key that changes shape inside the lock, and until recently it couldn’t be made.
Going in, a guide tool holds the access, the joint gets trimmed just enough to take the implant, and the implant rides down that same tool into place, gripping the bone above and the bone below. The company’s phrase for what that sets up is careful and deserves to stay careful: the conditions for fusion over time.
Over time, meaning the implant holds the joint still while your own bone does the fusing, over months, the way it always has.
A single access point per side. Two, where the old way needs six.
Before any of this went near a living person they took six spines from cadavers and bent them. Forward and back, side to side, twisting, every direction a lower back actually moves. Once with the spine untouched. Then again with the implant in, to see whether this little thing could hold a segment as still as the standard construct does.
The company says it did. Comparable or better than a standard pedicle screw construct, in their words.
And they built it for a particular room. Ambulatory surgery centers are where more and more American spine surgery is heading, and a six-incision construct doesn’t fit in one. This does.
Nine Out of Ten. The Next Morning, One.
The first person ever to get one was a 67-year-old woman in Hungary, in December 2018, at the University of Pécs, operated on by Professor Attila Schwarcz. She’d been living with severe back and leg pain and she rated it a nine out of ten.
The day after surgery she rated it a one.
At six months, zero.
The study’s principal investigator wrote to the company that next morning. She was doing extremely well and reporting no pain, he said, there had been practically no blood loss, and he could have discharged her that same day. “I can hardly believe it.”
One woman, one early case, and a single case is a beginning rather than a proof. But Schwarcz put the engineering case coldly afterward: since the implant never travels the pedicle road at all, it carries almost zero risk of causing nerve root injury.
Then came the unglamorous years. During the European trial, somebody from the company stood in the operating room for every single case. Every one of them. Watching surgeons handle their device, writing down what was awkward, then redesigning the instruments between surgeries and bringing the new ones to the next case.
That’s what a company looks like when it knows its device isn’t finished yet.
Somewhere in there a surgeon at Rambam in Haifa put both implants into a patient in under half an hour. Europe cleared it in 2021. On April 18, 2024, so did the FDA. The company says it has now started selling it in the United States.
The Screw That’s Still In There
The cleared system has a screw in it.
The company’s marketing leans hard on the word screwless, and for the American product that isn’t the full picture. The 510(k) summary describes a modular spacer plus a single trans-facet screw sold as one integrated construct, and the agency files the whole thing under a product code reading System, Facet Screw Spinal Device.
But look at which screw. It’s a small one, crossing the joint at the back, and the FDA record notes it’s near enough identical to one cleared in 2010. That’s King’s screw from 1948 and Magerl’s from 1984, still doing the one job it was always good at. What’s gone is the four pedicle screws and the road they travel, which was always the frightening part. The bending spacer is the only new thing in the box, and everything around it is old and proven, which is how an abandoned idea gets to come back at all.
Two more things you should know. The American clearance is narrow: one level, L3 to L5, for lumbar degenerative disc disease in patients who’ve already failed conservative care, and it must be accompanied by a cleared intervertebral body fusion device at the same level. In the United States this isn’t a standalone operation, and it isn’t cleared here for the wider set of conditions the company treats in Europe. Somebody with a severe high-grade instability, or a spine needing the long rigid correction rods are built for, is a different patient, and for them four screws and two rods may well be exactly right.
And the evidence is young. The clearance rests on a single-arm study, where everyone enrolled got the device and none of them were randomized against pedicle screws. Sixty years of data sit on the other side of that ledger. Dr. Isador Lieberman of the Texas Back Institute, who uses it, put it about as carefully as a surgeon will: for the right patients, a great alternative to pedicle screws.
For the right patients. If any of this is close to home the conversation that matters is with a spine surgeon who can look at your actual spine, and not with a Substack.
40 Years in Plain Sight
Nobody’s walking who couldn’t walk yesterday. This doesn’t restore anything, and I’d rather undersell it than have a surgeon email me. What it lowers is the price of admission.
There’s something here bigger than one implant. For 40 years, “you don’t fuse through the facet joint” was the settled answer, and every surgeon trained after about 1990 learned it that way, and they were taught correctly, because it was true. It was just never a verdict about the joint. It was a verdict about the lathe. The machine shop couldn’t make the part, that got written into practice, and a generation later nobody remembered where the limit came from. It was simply how spines are done.
Which makes me wonder what else is sitting on a shelf. There must be other good ideas in those journals, put down in the sixties and seventies for the same reason, and printing changed what can be made, and so did materials that didn’t exist 20 years ago. Somewhere in a stack of back issues somebody’s abandoned paper quietly became buildable and is still waiting for someone to walk past it with the right eyes. Magerl’s had been lying there since 1984, in plain sight, in every spine library in the world, and a whole profession stepped over it every year.
ZygoFix walked past one and stopped, and they aren’t finished. Their investor’s portfolio page lists the same implant for two more jobs. Your neck has facet joints, and so does the joint where your spine meets your pelvis.
So somewhere in America this year, somebody who has spent three years failing physical therapy is going to be told they need their spine fused. And in the right case, at the right level, that can now happen through two incisions instead of six. The muscle stays on the bone. The hardware stays out of the tunnel. The company says the procedure is suitable for an outpatient setting, which in plain terms means that person may get to sleep in their own bed that night rather than in a ward.
And the old operation tends to wreck a facet joint it was never trying to treat, roughly one placement in five, on its way past to somewhere else. A screw can sit entirely inside its pedicle and still catch the joint one level up, and the imaging in the room confirms the first thing without reliably showing the second. This one never goes up there at all. It works inside the joint it came for, because that joint was the destination all along.
They’ll never know the thing in their back came out of a business park an hour from the Lebanese border, designed by a man who took up medicine at 45 and failed at this twice before he got it right, and a surgeon who spent his last act making his own instruments unnecessary. Magerl was Swiss, and Magerl was right, and better engineers were never what this needed.
For 60 years the answer was a better screw.
Israel built a different shape.
Built in Israel. For everyone.
Nothing here is medical advice. The zLOCK Lumbar Facet Fixation System is FDA 510(k) cleared for temporary stabilization as an adjunct to a single-level interbody lumbar fusion from L3 to L5, for degenerative disc disease in skeletally mature patients who have failed conservative care, and must be used with a cleared intervertebral body fusion device at the same level. Clearance rests on substantial equivalence to devices already on the market, not on a trial proving it superior to pedicle screws. Biomechanical figures cited are cadaver bench data reported by the manufacturer. The first-in-human result is one early case, not a general outcome. It’s prescription-only and placed by a surgeon.